
Avulsion Fracture
Avulsion Fracture in Young Athletes
Avulsion fractures can affect active children and teenagers when a sudden, powerful muscle or ligament pull removes a small piece of bone from its attachment.


Avulsion fractures are particularly relevant to growing athletes because muscle strength can develop faster than some immature bone attachment areas. The injury commonly affects the pelvis and hip, although it can also occur around the knee, ankle and foot.
This injury sits within the broader youth sports injury group.
What Is an Avulsion Fracture?
An avulsion fracture is a bone injury where a tendon or ligament pulls away a small fragment of bone. In younger athletes, this often occurs near an apophysis, which is a growth-related area where a muscle or tendon attaches to bone.
During rapid growth, this attachment area may be more vulnerable to a sudden high-force pull than the surrounding muscle-tendon unit.
What Are the Symptoms of an Avulsion Fracture?
Symptoms usually begin suddenly during sport. A young athlete may feel sharp pain, a pulling sensation or sometimes a pop near a muscle attachment. They may struggle to continue running, kicking, jumping or walking normally.
Common signs include:
- sudden pain during sprinting, kicking, jumping or twisting
- local tenderness over a bony attachment point
- swelling or bruising near the injury
- limping or pain with walking and stairs
- pain when the attached muscle contracts or stretches
Why Do Avulsion Fractures Affect Growing Athletes?
Avulsion fractures are more common during adolescence because bones and their attachment areas are still developing while muscles are becoming stronger. A powerful contraction can overload the attachment point before it can tolerate the force.
Other growth-related conditions affecting active young people include Osgood-Schlatter disease, Sinding-Larsen-Johansson syndrome and Sever’s disease.
What Causes an Avulsion Fracture?
Avulsion fractures commonly occur during rapid acceleration, deceleration, landing, twisting or explosive kicking. Football, athletics, gymnastics, dancing and court sports can expose young athletes to these high forces.
Rapid changes in training load, fatigue and returning after time away may increase the demands placed on a growing athlete. However, an avulsion fracture usually occurs when a sudden high-force muscle contraction or sporting movement overloads the attachment site.
Similar symptoms can occur with a muscle strain or stress fracture, so assessment can help distinguish between these injuries.
Where Do Pelvic Avulsion Fractures Occur?
Pelvic avulsion fractures usually occur where powerful hip, thigh or trunk muscles attach to growing bone.
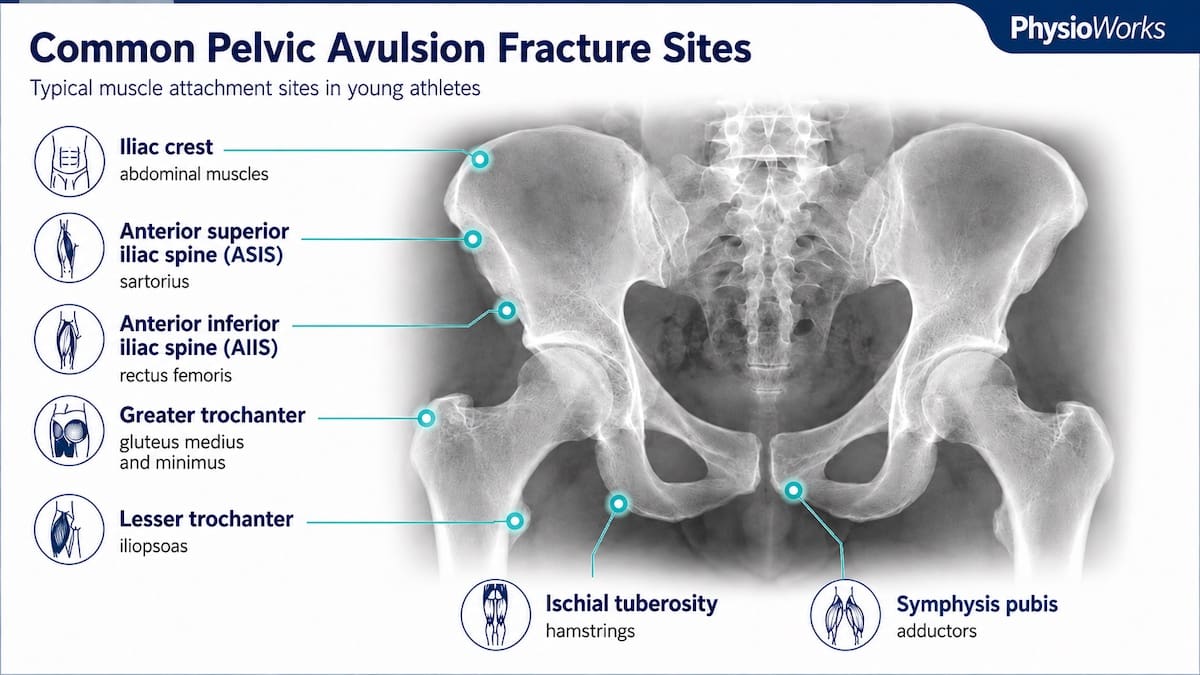
Common Pelvic Attachment Sites
- Iliac crest: abdominal muscle attachment
- Anterior superior iliac spine: sartorius attachment
- Anterior inferior iliac spine: rectus femoris attachment
- Ischial tuberosity: hamstring attachment
- Greater trochanter: gluteal muscle attachment
- Lesser trochanter: iliopsoas attachment
- Symphysis pubis: adductor attachment region
How Is an Avulsion Fracture Diagnosed?
A physiotherapist or doctor will consider how the injury happened, the exact pain location, swelling, tenderness, strength and pain with movement. Assessment may also include walking, muscle contraction and the athlete’s ability to load the injured area.
An X-ray is commonly used when a fracture is suspected and may show the bone fragment and any displacement. MRI, CT or ultrasound may sometimes be considered when symptoms strongly suggest an avulsion injury but initial imaging is unclear, or when more detail is required.
The NCBI StatPearls overview of avulsion fractures provides further medical information about injury patterns and assessment.
How Is an Avulsion Fracture Treated?
Most avulsion fractures in young athletes improve without surgery. Early management usually involves stopping painful sport, reducing load and protecting the injured area. Crutches or temporary offloading may help when walking is painful.
As symptoms settle, rehabilitation can gradually restore comfortable movement, flexibility and strength. Later stages may progress to running, hopping, jumping, kicking and change-of-direction activities when appropriate.
Orthopaedic review may be recommended when a fracture is substantially displaced, symptoms remain severe or recovery does not progress as expected. Rehabilitation commonly follows principles used in post-fracture physiotherapy.
How Long Does an Avulsion Fracture Take to Heal?
Many uncomplicated avulsion fractures improve over several weeks. However, recovery varies according to the fracture site, displacement, the athlete’s age, symptoms and sporting demands.
Walking often becomes comfortable before sprinting, kicking and jumping are ready. Therefore, return to sport should follow healing and functional progress rather than a fixed date alone.
How Does an Athlete Return to Sport?
Return to sport should progress in stages. Early rehabilitation may focus on comfortable walking, pain-free mobility and gentle muscle activation. Later stages rebuild strength, running tolerance and sport-specific control.
Before returning to unrestricted competition, the athlete should usually be able to:
- walk and use stairs without pain or limping
- complete relevant strength exercises with good control
- run, hop and change direction without symptoms
- complete progressively harder sport training without a significant symptom flare
The exact requirements depend on the injury site and the demands of the athlete’s sport.
Can Avulsion Fractures Be Prevented?
Avulsion fractures cannot always be prevented. Sensible training progression, appropriate conditioning, adequate recovery and early attention to recurring growth-related pain may help young athletes manage sporting load.
Parents, coaches and athletes should take repeated pain during sprinting, kicking or jumping seriously, particularly during a growth spurt.
When Should You Suspect an Avulsion Fracture?
Consider an avulsion fracture when a young athlete develops sudden localised pain during a sprint, kick, jump or twist and cannot load the area normally afterwards.
Arrange assessment when the athlete has:
- difficulty walking or a clear limp
- significant swelling or bruising
- marked tenderness over a bony attachment point
- pain that is not settling as expected
- pain that quickly returns when training resumes
What Should You Do Next?
If your child or teenage athlete has symptoms that suggest an avulsion fracture, stop the painful activity and arrange an appropriate assessment. This can help determine whether imaging, temporary protection or a rehabilitation program is required.
-
Stop painful sport
Avoid repeatedly testing sprinting, kicking, jumping or other movements that reproduce acute pain.
-
Protect the injured area
Reduce loading and use support such as crutches when advised if normal walking is painful.
-
Arrange assessment
Assessment can help distinguish an avulsion fracture from other muscle, tendon or bone injuries and determine whether imaging is appropriate.
-
Progress gradually
Build walking, strength, running and sport-specific activity progressively rather than returning directly to full training.
Choose your clinic and appointment pathway
Select a PhysioWorks clinic to continue to live booking, an appointment request or reception assistance.
Frequently Asked Questions About Avulsion Fractures
Can you walk on an avulsion fracture?
Some athletes can still walk, although pain may limit stride length, stairs, speed or pushing off. Being able to walk does not rule out an avulsion fracture. Assessment can help determine whether imaging or temporary offloading is appropriate.
How serious is an avulsion fracture?
Many avulsion fractures heal well with conservative care. The significance depends on the injury site, the amount of displacement, symptoms and functional loss. Severe pain, marked difficulty walking or substantial displacement requires closer medical review.
Do avulsion fractures need surgery?
Most adolescent avulsion fractures do not require surgery. Non-surgical management is common when displacement is limited and recovery progresses appropriately. Surgery may be considered for selected injuries with substantial displacement or persistent functional problems.
How long does an avulsion fracture take to heal?
Many uncomplicated avulsion fractures improve over several weeks, although full return to sprinting, kicking or jumping may take longer. Healing, symptoms, strength and sporting demands all influence the return-to-sport timeline.
Do avulsion fractures show on an X-ray?
Many avulsion fractures can be seen on X-ray, particularly when the bone fragment is displaced. Smaller injuries can be more difficult to identify. Further imaging may be considered when symptoms remain strongly suggestive despite an unclear initial X-ray.
References
- Ferraro SL, Batty M, Heyworth BE, Cook DL, Miller PE, Novais EN. Acute pelvic and hip apophyseal avulsion fractures in adolescents: a summary of 719 cases. J Pediatr Orthop. 2023;43(4):204-210.
- Yeager KC, Silva SR, Richter DL. Pelvic avulsion injuries in the adolescent athlete. Clin Sports Med. 2021;40(2):375-384. doi:10.1016/j.csm.2020.12.002.
- McCoy JS, Narducci CA. Avulsion fractures. StatPearls. Updated 2023.
- Eberbach H, Hohloch L, Feucht MJ, Konstantinidis L, Südkamp NP, Zwingmann J. Operative versus conservative treatment of apophyseal avulsion fractures of the pelvis in adolescents. BMC Musculoskelet Disord. 2017;18(1):162. doi:10.1186/s12891-017-1527-z.
