
Thoracic Facet Joint Pain
Thoracic Facet Joint Pain



Thoracic spine assessment for mid-back and rib pain.
Thoracic facet joint pain describes a pattern of mid-back pain that may involve the small joints at the back of the thoracic spine. Symptoms often change with twisting, arching, reaching, lifting, prolonged sitting or other movements that load the mid-back.
Some people describe the pain as sharp, catching or “grabby”. Others notice a more constant ache after sitting, driving or working in one position for a long time.
Thoracic spine symptoms may overlap with mid-back pain and rib pain because the spinal and rib joints work closely together.
Physiotherapy assessment can help determine whether your presentation is consistent with a mechanical thoracic pain pattern, identify contributing movement or loading factors and guide an appropriate rehabilitation plan.
What Is Thoracic Facet Joint Pain?
Thoracic facet joints are small paired joints at the back of each spinal segment. They help guide movement between the thoracic vertebrae and contribute to control of rotation, bending and extension.
A thoracic facet pain pattern may develop when a joint and its surrounding tissues become sensitive during movement or loading. Symptoms can start after a sudden movement, repetitive activity or prolonged posture, although there is not always one obvious trigger.
It is usually difficult to identify a single painful spinal structure from symptoms alone. Instead, your physiotherapist considers your history, symptom behaviour, movement findings and other possible causes before deciding on the most appropriate management plan.
Location
Pain is often felt in the mid-back and may sit slightly to one side of the spine.
Movement
Twisting, arching, reaching or changing position may reproduce symptoms.
Rib symptoms
Some people feel discomfort spreading towards the ribs or chest wall.
Sitting
Long periods of desk work, driving or sustained posture may aggravate symptoms.
Breathing
Deep breathing, coughing or sneezing can sometimes increase pain around the thoracic spine or ribs.
Assessment
Clinical assessment helps distinguish a mechanical thoracic presentation from other causes of chest, rib or back pain.
Where Are the Thoracic Facet Joints?
The thoracic spine sits between your neck and lower back. It contains 12 vertebrae, labelled T1 to T12. Your ribs also attach throughout this region.
Each thoracic segment includes two facet joints at the back of the spine. The spinal joints, discs, ribs, muscles and surrounding tissues work together during breathing, trunk rotation, reaching and upper-limb activity.
What Does Thoracic Facet Joint Pain Feel Like?
Symptoms often behave mechanically. In other words, the pain changes according to movement, position, load or activity.
- Localised aching or sharp pain in the mid-back.
- Pain slightly to one side of the spine.
- Discomfort with twisting or arching backwards.
- Pain with reaching, lifting or overhead activity.
- Stiffness after sitting, driving or remaining in one position.
- A catching or “grabby” sensation during sudden movements.
- Pain that spreads towards the ribs or chest wall.
- Protective muscle tightness around the symptomatic area.
These features are not unique to the facet joints. Rib joints, muscles, discs and other structures can produce similar symptoms, which is why the overall clinical pattern matters more than any single symptom.
Is Thoracic Facet Pain the Same as Costochondritis?
No. They involve different areas, although symptoms may sometimes overlap.
A thoracic facet pain pattern is more commonly associated with spinal movement such as twisting, extension, reaching or changing position. Costochondritis more commonly causes pain and tenderness around the rib cartilage towards the front of the chest.
However, symptom location alone cannot safely determine the cause of chest pain. Seek medical assessment when symptoms are severe, unexplained or associated with warning signs.
What Else Can Cause Mid-Back or Rib Pain?
Several conditions may produce symptoms similar to a thoracic facet pain pattern.
| Condition | Common pattern | Useful next step |
|---|---|---|
| Thoracic facet pain pattern | Mid-back pain that often changes with twisting, extension, reaching, lifting or sustained posture. | Clinical assessment, movement rehabilitation and graded return to activity. |
| Costochondritis | Pain or tenderness closer to the front of the chest around the rib cartilage. | Assessment is appropriate, with medical review when symptoms are severe or potentially non-musculoskeletal. |
| Rib stress fracture | Focal rib pain associated with repetitive loading, persistent coughing or some sporting activities. | Reduce aggravating load and arrange assessment. Imaging may be required when clinically indicated. |
| Thoracic outlet syndrome | Symptoms may involve the neck, shoulder or arm, including heaviness, pins and needles or symptoms with arm elevation. | Assessment of the neck, shoulder girdle, neurological and vascular features. |
What Can Cause a Thoracic Facet Pain Pattern?
A mechanical thoracic pain episode can develop when the spine and surrounding tissues are exposed to more movement, load or sustained positioning than they currently tolerate.
Possible contributing factors include:
- Prolonged desk work or driving.
- Repeated twisting, lifting or reaching.
- Sudden or unfamiliar activity.
- Changes in training or workload.
- Reduced thoracic or rib movement.
- Reduced trunk or upper-back endurance.
- Previous thoracic or rib injury.
- Age-related spinal joint changes.
Why Can Thoracic Pain Feel “Locked”?
People sometimes describe a sudden painful restriction in the thoracic spine as a joint feeling “locked”. This does not necessarily mean that a vertebra or facet joint is literally stuck or displaced.
Pain, protective muscle tension and sensitivity near the end of a movement can temporarily make rotation or extension feel restricted. The sensation may occur after a small twist, awkward reach, lifting task or prolonged position.
Gentle movement and progressive loading are often more useful than repeatedly forcing the painful direction.
Can Too Much Thoracic Movement Contribute to Pain?
Yes. Not every painful thoracic segment is simply “stiff”. Some presentations appear to involve repeated loading or reduced control around a region that is already moving adequately.
In these cases, repeatedly trying to increase mobility may not be the best strategy. Rehabilitation may instead focus on trunk endurance, strength, pacing and better control during the activities that provoke symptoms.
A personalised assessment helps decide whether your rehabilitation should emphasise mobility, control, strength or a combination of these factors.
Can Thoracic Facet Pain Cause Rib Pain?
Thoracic spinal and rib joints sit close together and move as a coordinated system. As a result, pain arising around the thoracic spine may sometimes spread laterally towards the ribs or chest wall.
People may notice symptoms during deep breathing, coughing, sneezing, rolling in bed or reaching overhead. However, rib and chest-wall pain also have other possible causes, so new or unexplained symptoms should not automatically be assumed to come from a facet joint.
How Is Thoracic Facet Joint Pain Assessed?
Your physiotherapist will usually begin by asking about the onset of your pain, its location, movements that aggravate or ease it, general health, recent activity and any warning signs.
The physical assessment may include:
- Thoracic rotation, extension and bending.
- Rib and breathing movement.
- Shoulder and neck movement when relevant.
- Functional tasks that reproduce your symptoms.
- Thoracic and rib joint sensitivity.
- Muscle strength and endurance.
- Neurological testing when indicated.
Imaging such as X-rays, CT scans or MRI may be appropriate when fracture, significant pathology or another diagnosis is suspected. Imaging can also show age-related changes that may not be responsible for a person’s symptoms.
For a medical overview of spinal facet-joint disorders, see the NCBI Bookshelf overview of facet joint disease.
How Can Physiotherapy Help?
Physiotherapy for a thoracic facet pain pattern usually aims to settle symptoms, restore comfortable movement and progressively rebuild tolerance for everyday activity, work, exercise or sport.
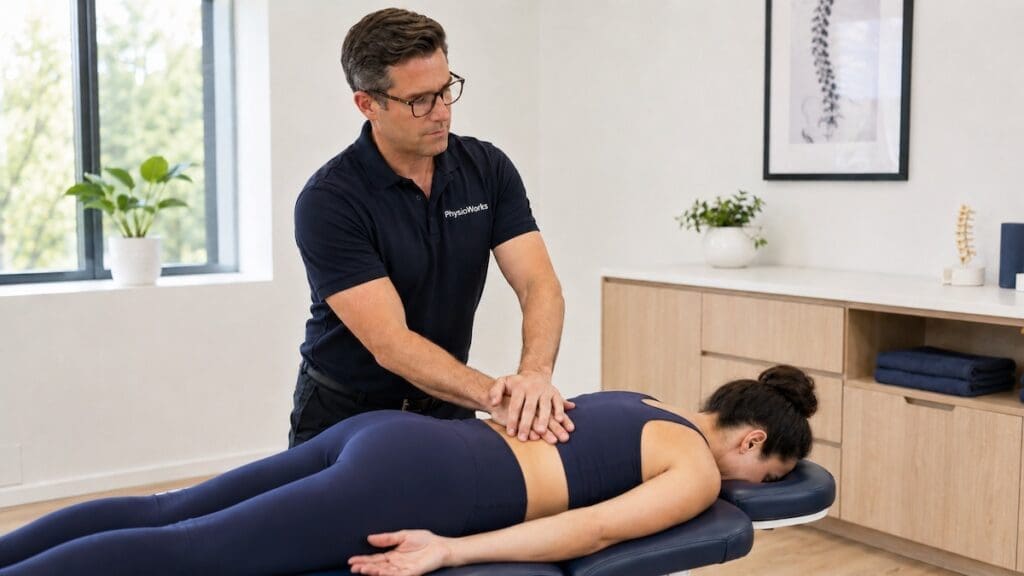
Thoracic mobilisation may be used selectively as part of a broader rehabilitation plan.
-
Settle the Irritable Phase
Early management usually focuses on keeping you comfortably active while reducing activities or positions that repeatedly aggravate the area.
Your physiotherapist may use education, activity modification, comfortable movement, soft tissue techniques or joint mobilisation when these help you move more easily.
-
Restore Comfortable Thoracic and Rib Movement
As symptoms settle, rehabilitation may include thoracic rotation or extension exercises, breathing-based rib movement and gradual exposure to the activities that previously provoked pain.
-
Rebuild Strength and Movement Control
Exercises may target the upper back, shoulder blades, trunk and other areas that help you tolerate lifting, reaching, sitting, training or work demands.
-
Return to Normal Activity
The final stage gradually restores the loads, positions and movements that matter to you. This may include gym training, overhead work, prolonged sitting, manual work or sport-specific activity.
Does Thoracic Manipulation Help?
Thoracic joint mobilisation or manipulation may produce short-term changes in pain or movement for some people. It is not required for everyone and should not be presented as putting a joint “back into place”.
When manipulation is clinically appropriate, it is generally used as one part of a broader plan that includes active movement, exercise and progressive return to normal loading.
Repeated passive treatment without progression towards active self-management is unlikely to address all of the factors contributing to recurrent symptoms.
What Can You Do Yourself?
For uncomplicated mechanical thoracic pain, gentle activity is usually preferable to prolonged rest.
- Change position regularly if sitting or driving aggravates symptoms.
- Keep moving within a comfortable range rather than repeatedly forcing painful movement.
- Use short bouts of walking or gentle thoracic movement during the day.
- Temporarily reduce movements or loads that repeatedly trigger sharp pain.
- Gradually restore lifting, reaching and exercise as symptoms allow.
- Follow an individual exercise program if one has been prescribed.
Exercises that build trunk and upper-body capacity may be useful for some presentations. See our core stability exercises guide for broader information.
What About Massage, Dry Needling or Other Treatments?
Massage
Soft tissue massage may provide short-term relief from protective muscle tension for some people. It should complement rather than replace movement and rehabilitation when these are needed.
Acupuncture and Dry Needling
Acupuncture or dry needling may provide short-term symptom relief for some people. Treatment response varies, and these approaches are usually most useful when they help you continue an active rehabilitation plan.
Injections and Radiofrequency Procedures
Persistent thoracic pain occasionally requires medical or specialist assessment. In carefully selected cases, doctors may consider diagnostic medial branch blocks or radiofrequency procedures.
These procedures are not routine treatment for a new episode of uncomplicated mechanical thoracic pain. Their suitability depends on the diagnosis, duration of symptoms, previous treatment and individual medical circumstances.
How Long Does Thoracic Facet Joint Pain Take to Settle?
Recovery varies. A recent mechanical episode may improve relatively quickly, while persistent or recurrent symptoms can take longer to settle and may require a gradual rebuilding of movement tolerance and strength.
Your progress can be influenced by:
- how long symptoms have been present;
- the original trigger and current workload;
- sleep and general health;
- work and sporting demands;
- other spinal or rib conditions; and
- how consistently activity is progressed.
Improvement does not require every spinal movement to feel completely symptom-free before activity resumes. Rehabilitation usually progresses according to function, tolerance and overall symptom behaviour.

Guided thoracic movement can help restore comfortable movement and build confidence with activity.
Related Thoracic and Spine Information
Thoracic Facet Joint Pain FAQs
What does thoracic facet joint pain feel like?
A thoracic facet pain pattern often feels like localised aching, sharp or catching pain in the mid-back. It may sit slightly to one side and become more noticeable with twisting, extension, reaching, lifting or prolonged positions. Other thoracic conditions can produce similar symptoms.
Can thoracic facet joint pain cause rib pain?
Thoracic spine pain can sometimes spread towards the ribs or chest wall because the spinal and rib joints are closely connected. However, rib and chest pain have several possible causes, so new or unexplained symptoms should be assessed rather than automatically attributed to a facet joint.
How is thoracic facet joint pain diagnosed?
There is no single physical test that confirms a thoracic facet joint as the source of pain. A physiotherapist assesses your history, symptom behaviour, spinal and rib movement, functional tasks and other relevant findings to determine whether the presentation is consistent with mechanical thoracic pain and whether further medical investigation is needed.
What helps thoracic facet joint pain?
Management may include activity modification, comfortable thoracic movement, exercise, progressive strengthening and a gradual return to normal activity. Joint mobilisation, manipulation or soft tissue treatment may provide short-term relief for selected people but are usually combined with active rehabilitation.
Can a thoracic facet joint really become locked?
People often use the word “locked” to describe sudden pain and restricted movement. This does not necessarily mean a spinal joint is literally stuck or displaced. Pain, muscle guarding and sensitivity near the end of movement can temporarily make the thoracic spine feel restricted.
When should I worry about mid-back or chest-wall pain?
Seek emergency medical care for new chest pressure or tightness, significant shortness of breath, fainting, heavy sweating with chest symptoms, or pain spreading into the jaw or arm. Prompt medical assessment is also appropriate after severe trauma or with fever, unexplained weight loss, new neurological symptoms, severe unexplained night pain or rapidly worsening symptoms.
What to Do Next
If mid-back or rib pain is limiting your movement, work, sleep or exercise, a physiotherapy assessment can help determine the most likely contributors and whether your presentation is suitable for physiotherapy management.
Your plan can then focus on the movement, strength, activity and symptom-management strategies that are most relevant to you.
Choose your clinic and appointment pathway
Select a PhysioWorks clinic to continue to live booking, an appointment request or reception assistance.
Thoracic and Upper Back Products
These thoracic and upper back products are commonly used by our physiotherapists to improve strength, posture, movement, plus assist home exercise programs.
-
 Back, Braces & Supports, Posture
Mueller Green Adjustable Back Abdominal Support
$125.00Add to cartQuick View -

-
-
-
-

 Exercise Balls, Back, Exercise Equipment, Knee, Shoulder
66fit Exercise Balls | Core & Rehab Stability Ball
$32.00 – $57.00Select optionsQuick View -
-
- Liniments & Gels, Massage Liniments, Pain Management
Fisiocrem
$16.95 – $39.95Select optionsQuick View - EMS Machines, Pain Management, TENS Machine, TENS Machine & EMS
NeuroTrac Rehab (TENS Machine + EMS)
$285.00Add to cartQuick View -
-

 Ice & Heat, Pain Management, Uncategorized
PhysiPak Universal Heat pack
$79.00Select optionsQuick View
















References
-
Curtis L, Dua A, Shah N, Padalia D. Facet Joint Disease. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2025 Jan–.
-
Waxenbaum JA, Reddy V, Margetis K. Anatomy, Back, Thoracic Vertebrae. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2026 Jan–.
-
Yoo YM, Kim KH. Facet joint disorders: from diagnosis to treatment. Korean J Pain. 2024;37(1):3-12. doi:10.3344/kjp.23228.
-
Manchikanti L, Knezevic E, Knezevic NN, et al. The effectiveness of medial branch blocks and radiofrequency neurotomy in managing chronic thoracic pain: a systematic review and meta-analysis. Pain Physician. 2023;26(5):413-435.
