
FHL Tendinopathy
FHL Tendinopathy (Flexor Hallucis Longus)
FHL tendinopathy can cause pain behind the inside ankle, through the arch or near the big toe, particularly during repeated push-off, running, jumping and dance.


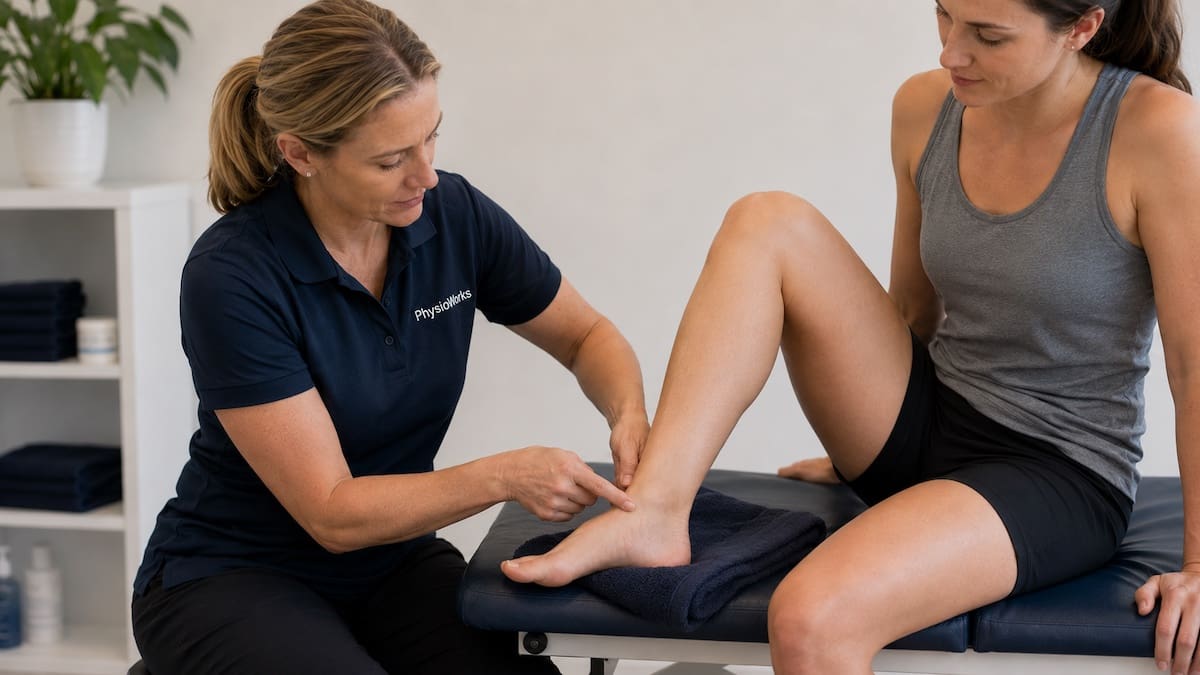
Assessing the FHL tendon path behind the inside ankle.
The flexor hallucis longus, or FHL, tendon helps you push off when you walk, run, jump or rise onto your toes. Symptoms may develop when the tendon is repeatedly exposed to more load than it can currently tolerate.
FHL tendon pain can overlap with other foot pain conditions, ankle pain and broader tendinopathy problems. A physiotherapist can assess the likely pain source, review your activity demands and guide an appropriate rehabilitation plan.
FHL Tendinopathy at a Glance
Common pain area
Behind the inside ankle, through the arch or near the base of the big toe.
Common triggers
Pointe work, hills, sprinting, jumping, hopping and repeated forefoot push-off.
Possible symptoms
Pain, stiffness and sometimes clicking, catching or creaking along the tendon path.
Early management
Modify aggravating load while maintaining suitable activity, then progressively rebuild tendon capacity.
Assessment
Consider physiotherapy assessment when symptoms limit activity, recur with loading or remain difficult to manage.
What Is FHL Tendinopathy?
FHL tendinopathy is a painful tendon condition involving the flexor hallucis longus tendon. The tendon passes behind the inside ankle, travels beneath the foot and attaches towards the big toe.
The FHL contributes to big toe flexion and forefoot push-off. It works during walking, running, jumping and ballet movements such as demi-pointe and pointe. Symptoms may develop when activity demands rise faster than the tendon can adapt.
You may also hear the term FHL tenosynovitis. This refers to inflammation or irritation involving the sheath surrounding the tendon. Tendon and tendon-sheath problems can produce similar symptoms and may occur together.
Where Does FHL Tendon Pain Usually Occur?
FHL tendon pain commonly occurs behind the inside ankle, through the arch or near the base of the big toe. Some people notice one main tender area, while others experience symptoms at several points along the tendon path.
- Pain behind or below the inside ankle bone.
- Arch pain during forefoot push-off or toe flexion.
- Pain near the base of the big toe.
- Stiffness after rest or when first starting activity.
- Clicking, catching or creaking behind the ankle in some cases.
Similar symptoms can occur with posterior ankle impingement, tarsal tunnel syndrome, plantar fasciitis and a foot stress fracture. Assessment can help distinguish between these possibilities.
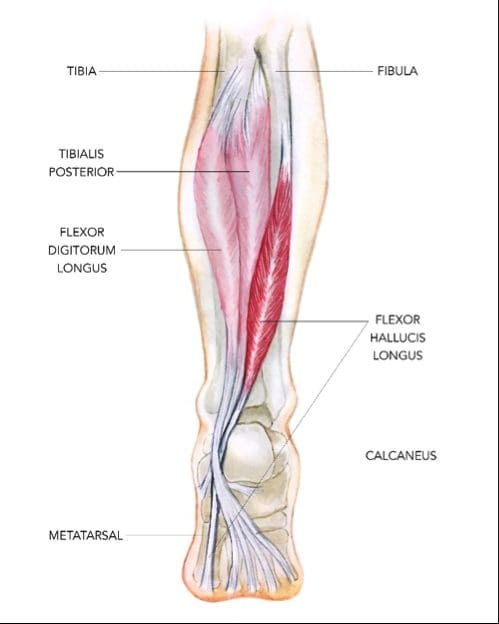
The FHL tendon travels behind the ankle and beneath the foot.
Who Gets FHL Tendinopathy?
FHL tendon pain is particularly relevant to activities that repeatedly load the forefoot, big toe and calf. It is well recognised in dancers but can also affect runners, athletes, active adults and people whose work involves prolonged standing or walking.
- Ballet dancers performing demi-pointe, pointe work, jumps and repeated turns.
- Runners, particularly when hills, speed or training volume increase.
- People involved in jumping, gymnastics, football, skating or diving.
- Dancers managing recurrent ballet injuries or other dance injuries.
- People returning to demanding activity after injury, illness or a training break.
- Workers who spend prolonged periods standing or walking.
The activity itself does not necessarily cause the problem. More often, symptoms develop when current tendon capacity and repeated loading demands become poorly matched.
What Can Contribute to FHL Tendinopathy?
FHL tendinopathy often develops after a change in loading. Several training, movement and footwear factors may contribute, although their importance varies between individuals.
Training and activity factors
- Rapid increases in running distance, speed or hill training.
- Increased pointe work, rehearsals, jumps or performance schedules.
- A sudden return to high-load activity after time away.
- Repeated loading with inadequate recovery.
- Changes in surface or activity demands.
Strength and movement factors
- Reduced calf strength or endurance.
- Reduced foot and ankle control during single-leg tasks.
- Restricted ankle or big toe movement where this alters loading.
- Foot posture or movement patterns that increase FHL loading in some people.
- Previous ankle, foot or calf injury affecting capacity.
Footwear factors
- Worn footwear.
- Sudden footwear changes.
- Sport, dance or work footwear that changes forefoot loading.
Management should consider the whole loading picture rather than one isolated factor. Depending on your assessment, this may include footwear advice, active foot posture correction exercises, mobility work and progressive strengthening.
Can You Keep Training With FHL Tendon Pain?
Some people can continue modified training while the tendon recovers. The appropriate amount depends on symptom severity, the activity involved and how the tendon responds during and after loading.
Mild symptoms settle quickly
You may be able to maintain a stable amount of activity while monitoring the response.
Pain rises with hills, jumping or pointe work
Reduce the aggravating component and rebuild it progressively rather than repeatedly provoking symptoms.
Pain changes your movement
Reduce or stop the provoking activity when pain causes limping or substantially changes your normal technique.
Catching, locking or significant swelling
Arrange assessment to check whether another tendon, tendon-sheath or ankle problem needs consideration.
How Is FHL Tendinopathy Diagnosed?
FHL tendinopathy is usually assessed from your symptom history and physical examination. A physiotherapist may check the course of the tendon, big toe movement and strength, ankle mobility, calf capacity and the activities that reproduce your symptoms.
Your assessment may include:
- Palpation along the FHL tendon behind the inside ankle and beneath the foot.
- Resisted big toe flexion and movement testing.
- Ankle movement and calf-strength assessment.
- Single-leg heel raises and balance tasks.
- Walking, hopping, running or dance-specific movement where appropriate.
- Review of recent training changes, footwear and activity demands.
Ultrasound or MRI may sometimes help when the diagnosis remains uncertain, symptoms persist despite appropriate management, or another tendon, tendon-sheath or structural problem is suspected. A scan is not required for every presentation.
How Can Physiotherapy Help FHL Tendinopathy?
Physiotherapy management usually focuses on identifying aggravating loads, maintaining suitable activity and progressively rebuilding the capacity required for walking, work, running, dance or sport.
Load management
Your physiotherapist may help modify running volume, hills, speed work, pointe work, jumping, rehearsals, gym exercises or prolonged standing. The aim is not necessarily complete rest. Instead, loading is adjusted to a level the tendon can tolerate while rehabilitation progresses.
Exercise and tendon loading
Progressive strengthening may include calf exercises, big toe flexor loading, foot-control tasks, balance exercises and later-stage hopping or activity-specific drills. Our tendon healing guide explains the broader principles of tendon loading and recovery.
Mobility and hands-on treatment
Where relevant, treatment may address calf, ankle or foot mobility and symptoms that make exercise difficult. Hands-on treatment can be used as an adjunct, but progressive loading and restoration of activity capacity remain important parts of rehabilitation.
Footwear, taping and support
Temporary taping, footwear modification or other support may help some people manage symptoms while strength and loading tolerance improve. These options should be matched to the individual rather than used automatically.
Medical review when needed
Medical review may be appropriate when symptoms are severe, the diagnosis remains uncertain, progress is poor despite a well-structured rehabilitation programme or another condition is suspected. Surgery is generally considered only for selected persistent or mechanically complicated presentations.
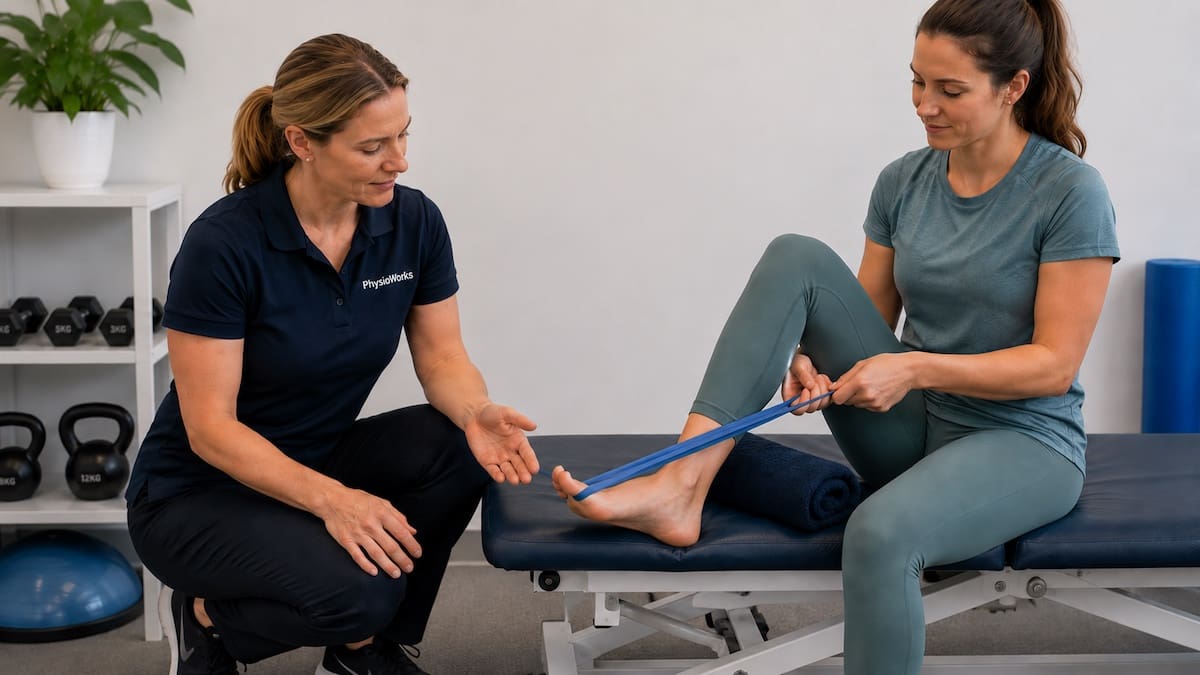
Progressive loading can help rebuild capacity for big toe flexion and push-off.
FHL Tendinopathy Rehabilitation Progression
Rehabilitation generally progresses from tolerable everyday loading towards greater strength and then the higher forces required for running, jumping or dance. Progress should reflect symptoms, strength, movement control and the demands of your chosen activity.
-
Settle the most aggravating load
Modify movements or training loads that repeatedly provoke symptoms while maintaining comfortable activity where possible.
-
Rebuild strength and control
Progress calf, foot and big toe flexor loading according to your current tolerance and assessment findings.
-
Reload push-off
Introduce greater single-leg demand, balance, faster calf work, hopping or other tasks required for your activity.
-
Return to full activity
Gradually rebuild running, jumping, pointe work or sport-specific loading while monitoring symptoms and function.
How Long Does FHL Tendinopathy Take to Improve?
Recovery varies. FHL tendinopathy often improves gradually over weeks to months rather than according to one fixed timetable. Symptom duration, tendon irritability, training demands, strength deficits and the ability to modify aggravating load can all influence progress.
Recovery may also fluctuate. A temporary increase in symptoms does not automatically mean further tendon damage, but repeated or progressively worsening flare-ups can indicate that the current loading progression needs adjustment.
Can You Reduce the Risk of FHL Tendinopathy?
No strategy can prevent every episode of FHL tendon pain. However, maintaining capacity and avoiding abrupt changes in high-load activity may reduce unnecessary tendon overload.
- Increase running, jumping or pointe-work demands progressively.
- Maintain calf and foot strength appropriate to your activity.
- Allow recovery between demanding training sessions.
- Rebuild higher-load activity progressively after a break.
- Replace badly worn footwear and review footwear when activity demands change.
- Use an appropriate warm-up before demanding sport, dance or running sessions.
When Should You Seek Assessment?
Consider physiotherapy assessment when pain is limiting walking, running, dance, work or sport, when symptoms repeatedly return as loading increases, or when you are uncertain about the cause.
Related Foot, Ankle and Tendon Articles
- Common Tendon Injuries – learn about common tendon symptoms and management principles.
- Foot Pain Conditions – explore other common sources of foot pain.
- Ankle Pain Conditions – explore ankle injury and overload conditions.
- Tendon Healing Guide – understand tendon loading, symptoms and rehabilitation.
- Active Foot Posture Correction Exercises – learn exercises used to develop foot and ankle control.
- Running Injuries – explore common running-related injury and overload problems.
- Ballet Injuries – read about foot, ankle and other dance-related conditions.
- Sports Physiotherapy – learn about assessment, rehabilitation and return-to-sport planning.
For a broader clinical overview, see the American Family Physician review of foot and ankle tendinopathies.
FHL Tendinopathy FAQs
Is FHL tendinopathy serious?
FHL tendinopathy is often manageable with appropriate load modification and rehabilitation. Assessment becomes more important when symptoms are worsening, causing altered movement, or associated with swelling, catching or locking.
Can I keep running with FHL tendon pain?
You may be able to continue modified running if symptoms remain mild and settle after loading. Reduce hills, speed, distance or frequency if pain progressively increases, alters your running pattern or remains aggravated afterwards.
What makes FHL tendon pain worse?
FHL tendon pain can worsen with activities requiring repeated forefoot push-off or big toe flexion. Common examples include hills, sprinting, jumping, hopping, calf raises and ballet pointe work.
Do I need a scan for FHL tendinopathy?
Not always. Many presentations can be assessed from the history and physical examination. Ultrasound or MRI may be considered when symptoms are unclear, persistent or severe, or when another tendon or structural problem is suspected.
How long does FHL tendinopathy take to heal?
There is no single healing time for FHL tendinopathy. Improvement commonly occurs gradually over weeks to months, while longer-standing or high-demand cases may require a longer rehabilitation period.
Can FHL tendinopathy affect ballet pointe work?
Yes. Demi-pointe and pointe work place substantial demand on the calf, big toe and FHL tendon. Symptoms may therefore appear or increase during repeated pointe work, jumps or other dance-specific loading.

Testing forefoot push-off as higher-load activity is progressively reintroduced.
What To Do Next
Choose your clinic and appointment pathway
Select a PhysioWorks clinic to continue to live booking, an appointment request or reception assistance.
Helpful Foot and Ankle Products
Some people use simple rehabilitation or support products while managing foot and ankle symptoms. The most suitable option depends on the problem, activity demands and stage of rehabilitation, so ask your physiotherapist when you are unsure what is appropriate.
Feet Products
These feet products are commonly used by our physiotherapists to improve support, comfort, strength, balance, flexibility, and home exercise programs.
-
- Liniments & Gels, Massage Liniments, Pain Management
Fisiocrem
$16.95 – $39.95Select optionsQuick View -


-


-

-
-
- EMS Machines, Pain Management, TENS Machine, TENS Machine & EMS
NeuroTrac Rehab (TENS Machine + EMS)
$299.95Add to cartQuick View -

 Ankle, Braces & Supports, Foot, Walking
Victor Moonboot 1.0 Air or No Air
$77.00 – $79.00Select optionsQuick View -
-
-
-
-

-
-

 Ankle, Braces & Supports, Calf, Foot
Orthosleeve Compression Bracing Socks
$49.00Select optionsQuick View














References
- Mikkelsen P, Andersen A, Shih HJS, Rowley KM, Kulig K. Flexor hallucis longus tendon morphology in dancers clinically diagnosed with tendinopathy. J Ultrasound. 2024;27:41–49.
- Michelson JD, Bernknopf JW, Charlson MD, Merena SJ, Stone LM. What is the efficacy of a nonoperative program including a specific stretching protocol for flexor hallucis longus tendonitis? Clin Orthop Relat Res. 2021;479(12):2667–2676. doi:10.1097/CORR.0000000000001867
- Deu RS, Deu SA. Tendinopathies of the foot and ankle. Am Fam Physician. 2022;105(5):479–488.
- Scott A, Squier K, Alfredson H, et al. ICON 2019: International Scientific Tendinopathy Symposium Consensus: clinical terminology. Br J Sports Med. 2020;54(5):260–262.
